Case study · Juva Health
No clinician in the room
Biofeedback is a proven migraine treatment that barely exists; Juva Health set out to deliver it through a phone. My job for two years was the delivery itself: turning the program our chief medical officer ran, in-person, into an app that carries her judgment. This page walks through the how: the program’s structure, its instruments, its copy, and the one problem I never got to solve.
- Role
- Co-Founder, Product Design Leader
- Team
- Four-person core — CEO, CTO, chief medical officer, me — plus one contractor-type designer or specialist at a time
- Shipped
- App Store, June 2020Public launch, April 2021juvahealth.com, archived April 202190-day program, Sept 2021, as the 12 Week Plan
- Timeline
- 2019–2021
The symptoms were the requirements
Biofeedback works for migraine, and almost nobody gets it: roughly 700 certified headache specialists serve the 39 million people in the US who live with the condition. A phone can reach people those 700 never will. It also delivers the therapy through a screen and a pair of headphones, to someone whose symptoms are set off by light and sound.
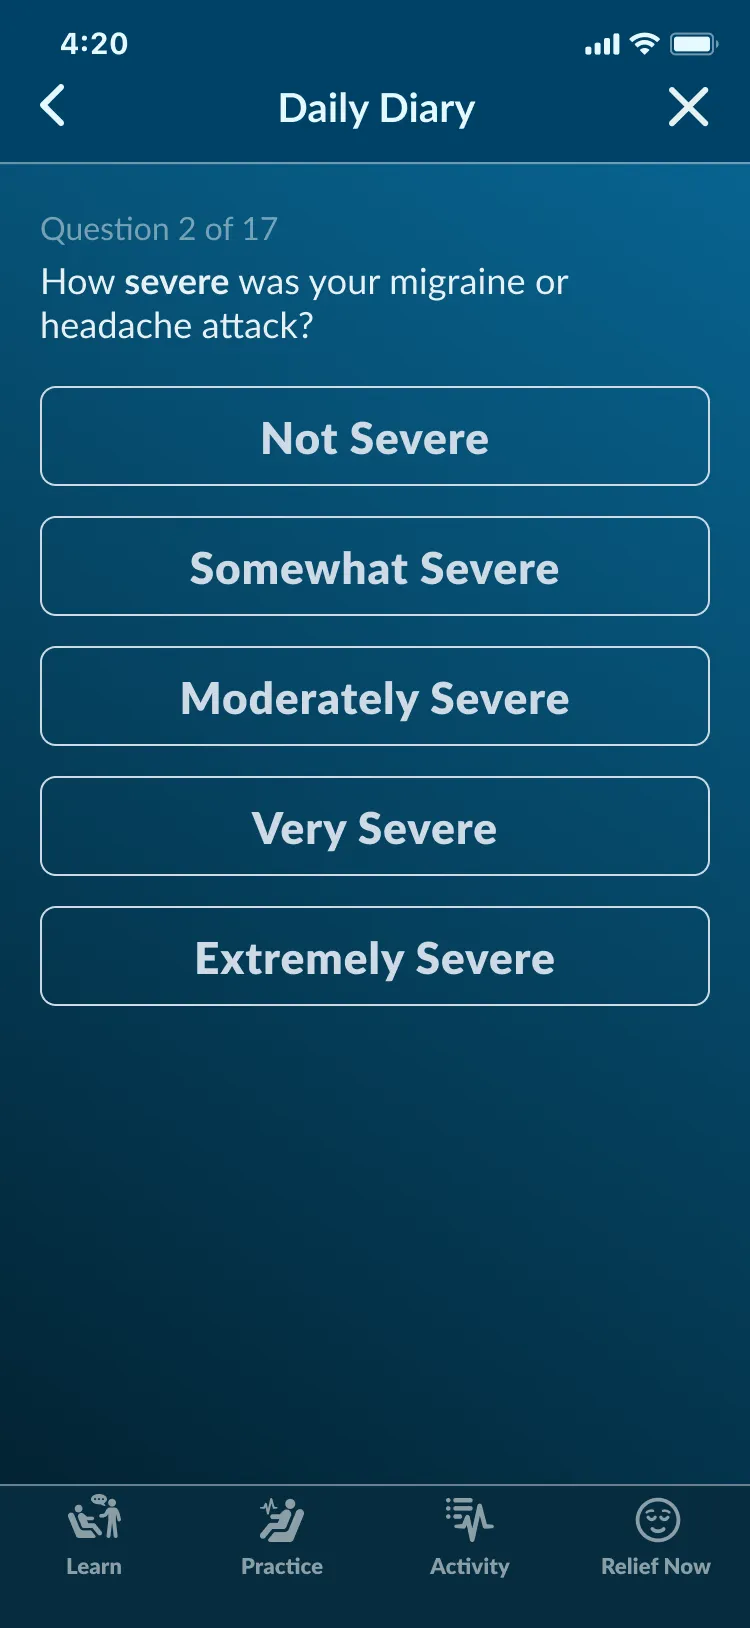
In April 2019, before there was any code, I turned the symptom list into design requirements. Audio sensitivity made the volume slider the most prominent control on the screen. Cognitive impairment meant every screen had to work for someone who could barely think. At the end of that month the CEO wanted qualifying questions before anyone could get in; I argued for no barrier at all, because someone may have “stumbled across this on the app store and downloaded it in a moment of desperation.” An outside advisor agreed with me, and the questions never shipped. Delivery meant everything from contrast ratios to the shape of a phone stand.


A protocol, not a content calendar
In September 2020 I wrote up a two-week beta with five users, and the report opens with what didn’t work: only one of the five practiced as often as we recommended, and only one reported any real change in her migraine activity. What people liked doesn’t appear until page two. The explore list at the end reads now like the following year’s roadmap: darker palettes for light sensitivity, a gooseneck stand so someone could practice lying down, locking content until the prerequisite was done, reminders to practice. Three months later I specced the answer to the adherence number, and it wasn’t a screen. It was a program whose stated goal was usage and retention.
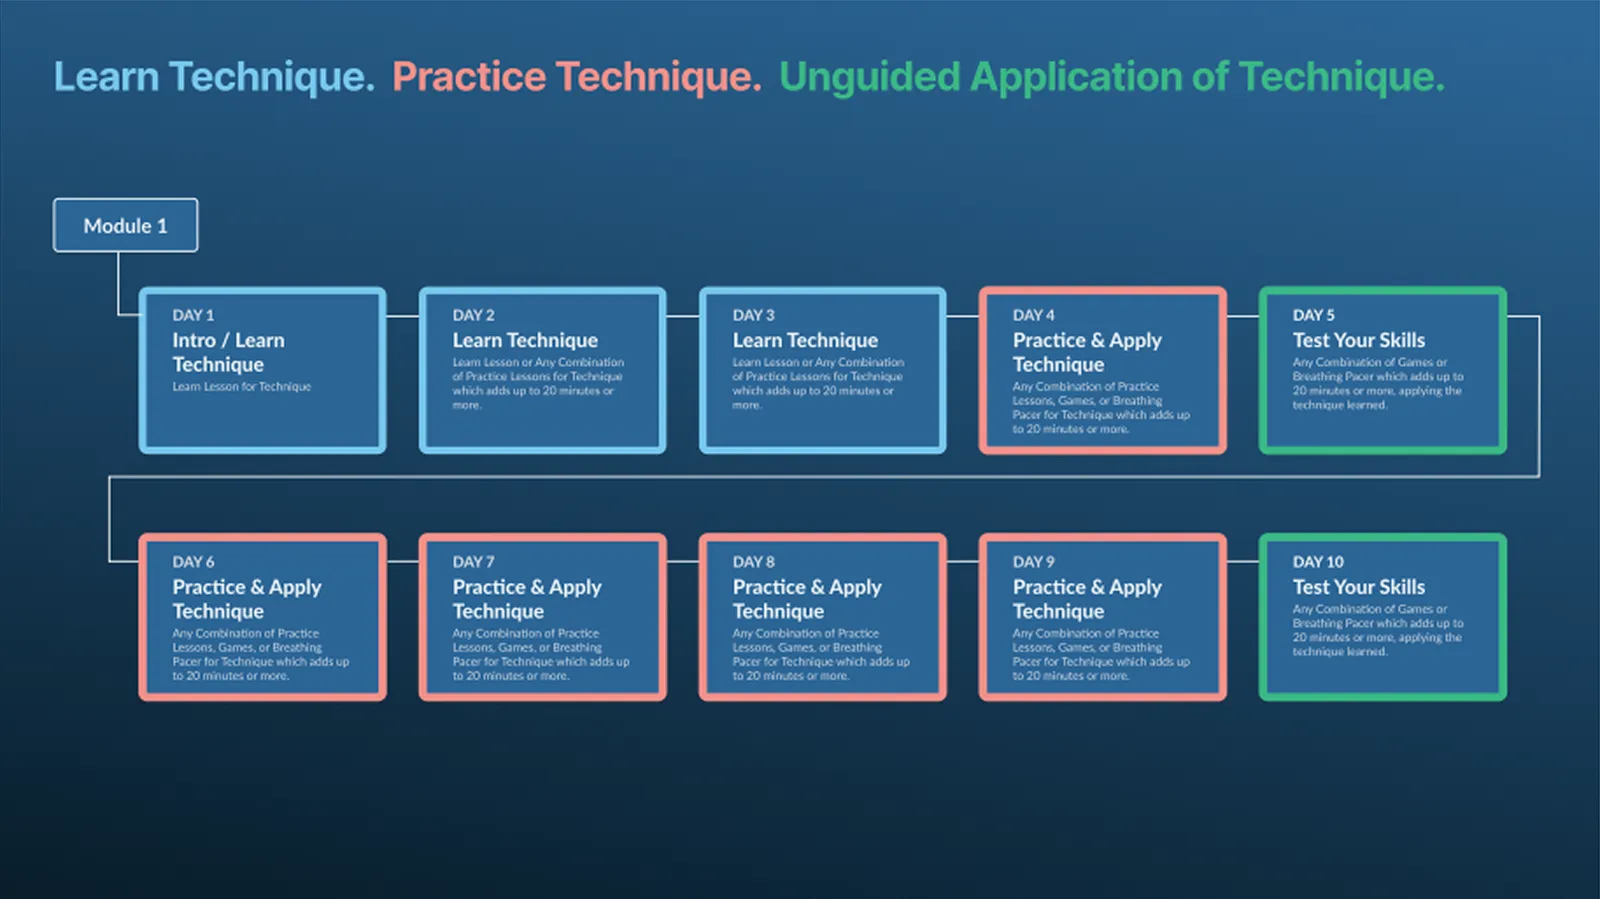
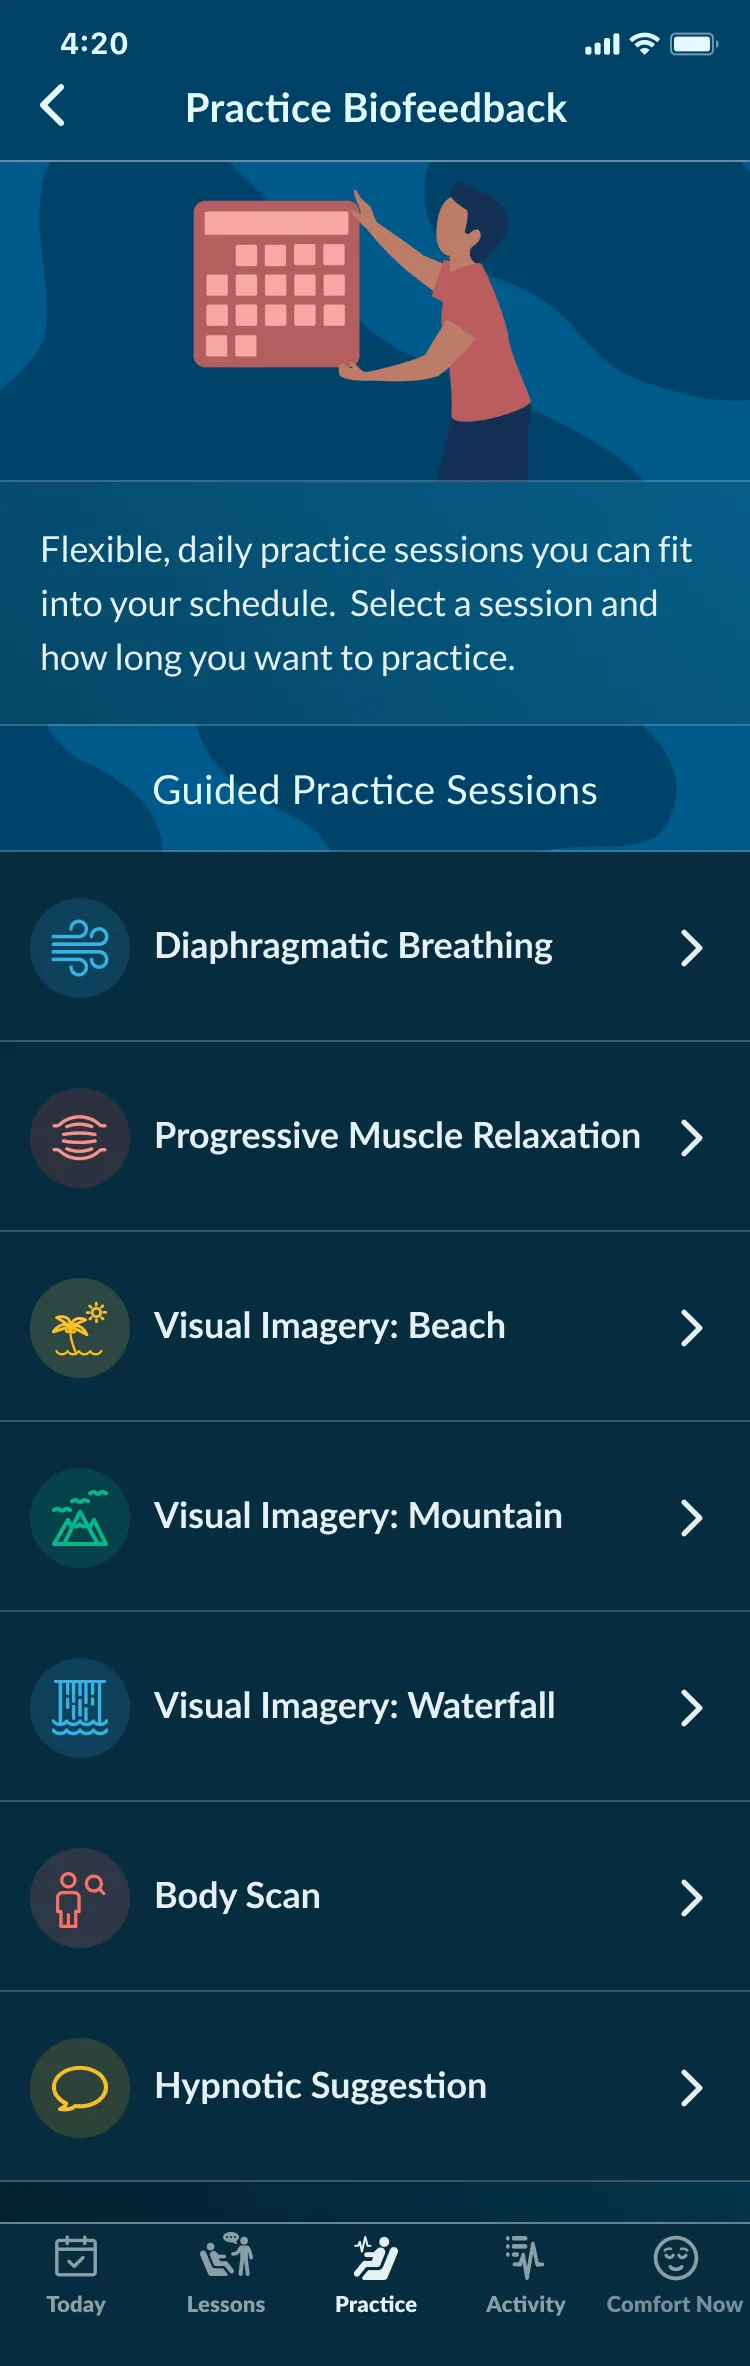
The 90-day program is nine modules of ten days each. Every module follows the arc a clinician would run: learn the technique, practice it guided, then apply it on your own; those unguided days double as assessment checkpoints. Progress is decoupled from the calendar. A “day” is a unit of work with one to three real days to complete it; miss longer and you repeat the day; take a week off and you redo the module, because that’s what a clinician would have you do once a skill has decayed.
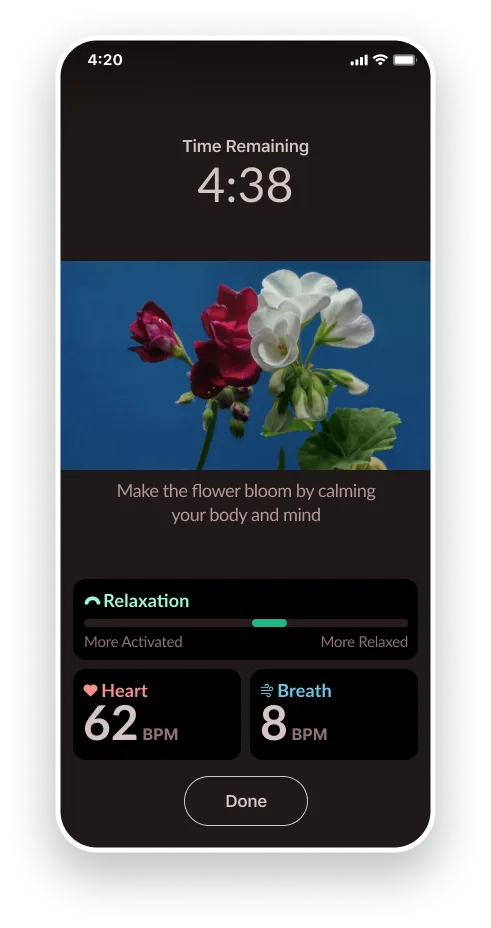
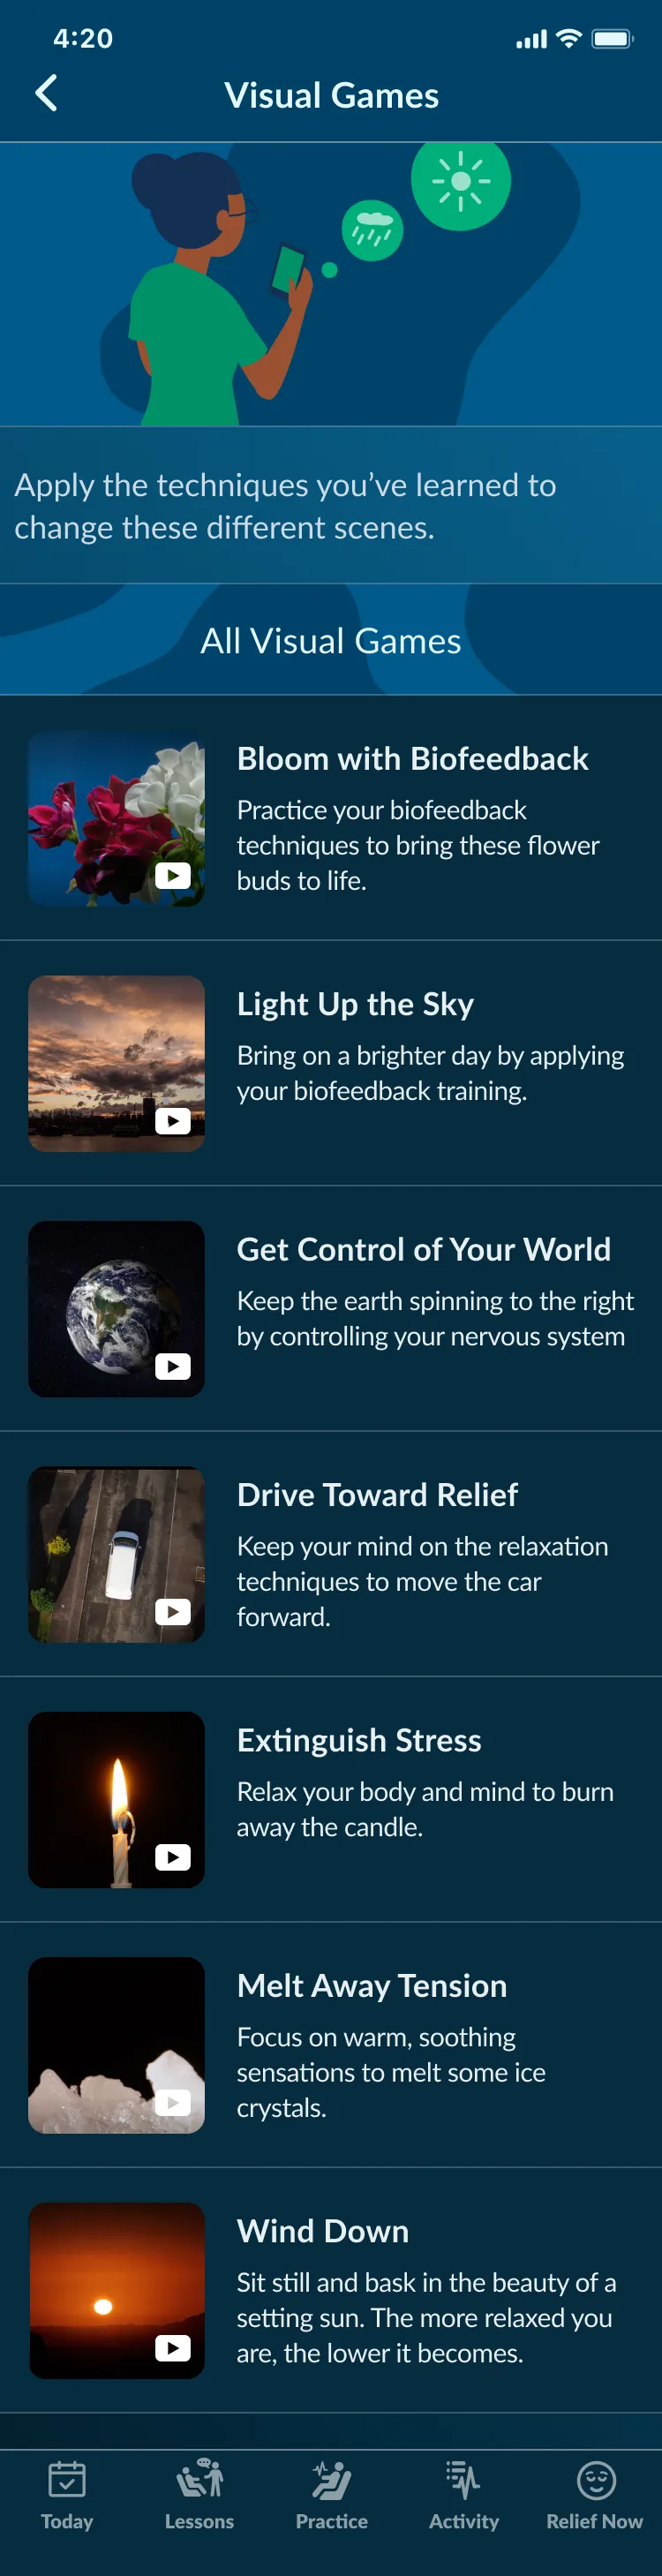
Consistency is rewarded with content, not celebration: finish on schedule and new games unlock. The games work the same way: you win by lowering your heart rate, and there is no score, badge, streak, confetti, or reward sound. Each is a light, motion, or audio event aimed at someone who can be hurt by all three.
And because the judgment being written down wasn’t mine, every parameter (module order, days per module, what happens on a given day) is editable by the clinicians.


What I claim
I resigned in May 2021, and that September the company shipped it as the 12 Week Plan, built from the files I handed over; no adherence or retention data for it has ever been in my hands.
What my own beta report named as the measure: empirical evidence of migraine frequency and reduction, and frequency of use.
Documented rows have a dated artifact I can produce on request.
Instruments that can’t call you a failure
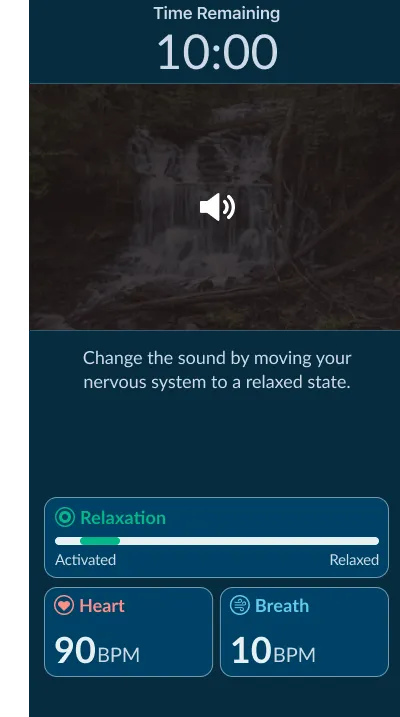
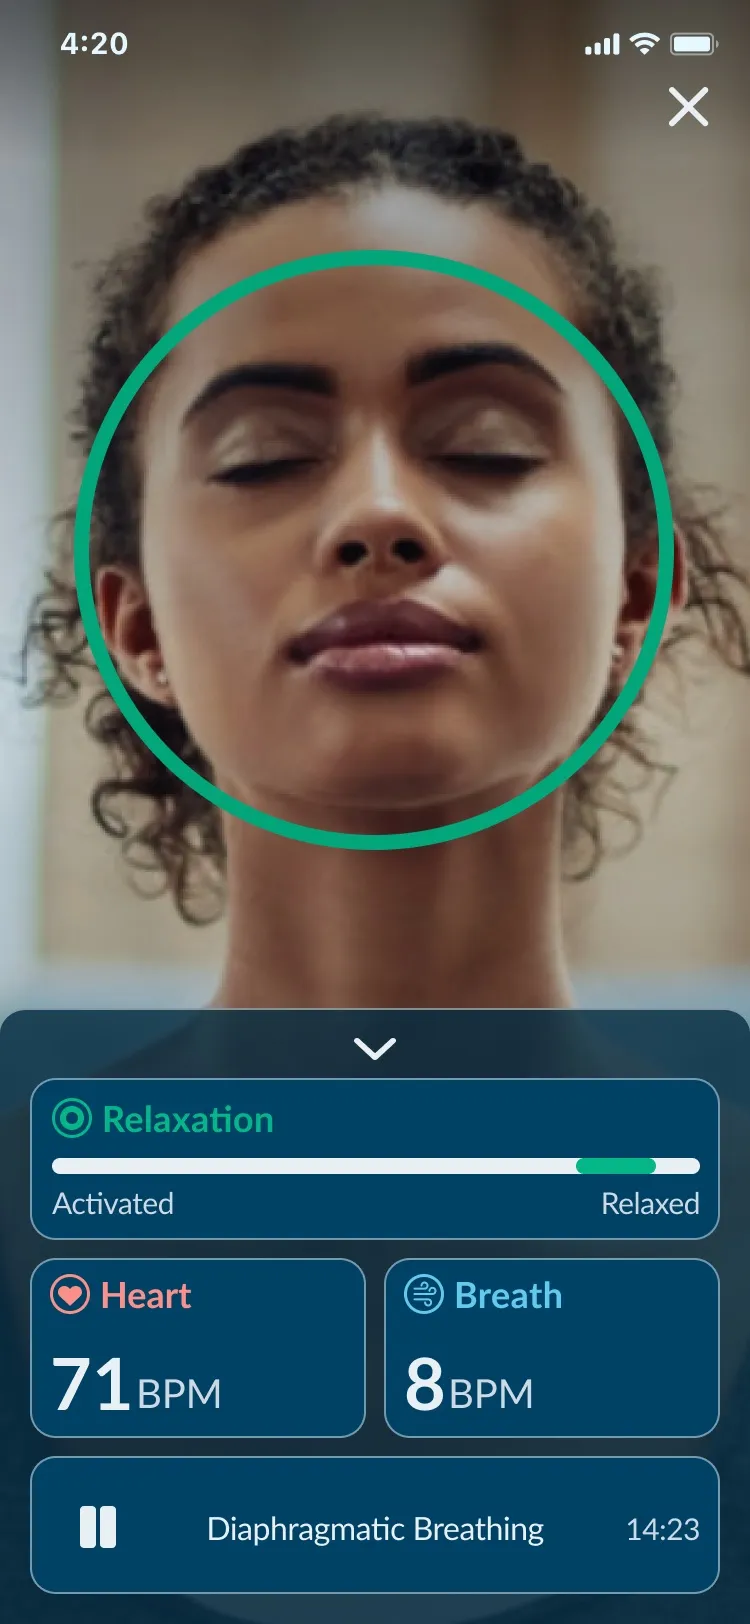
The relaxation gauge went through the argument that defined the whole product. The first version was a literal car-style dial, which turns a therapy session into a performance readout. What shipped is a minimal bar that stays green at every position: it measures how relaxed you are, not whether you’re activated or relaxed, so there’s no end of it you can be failing at.
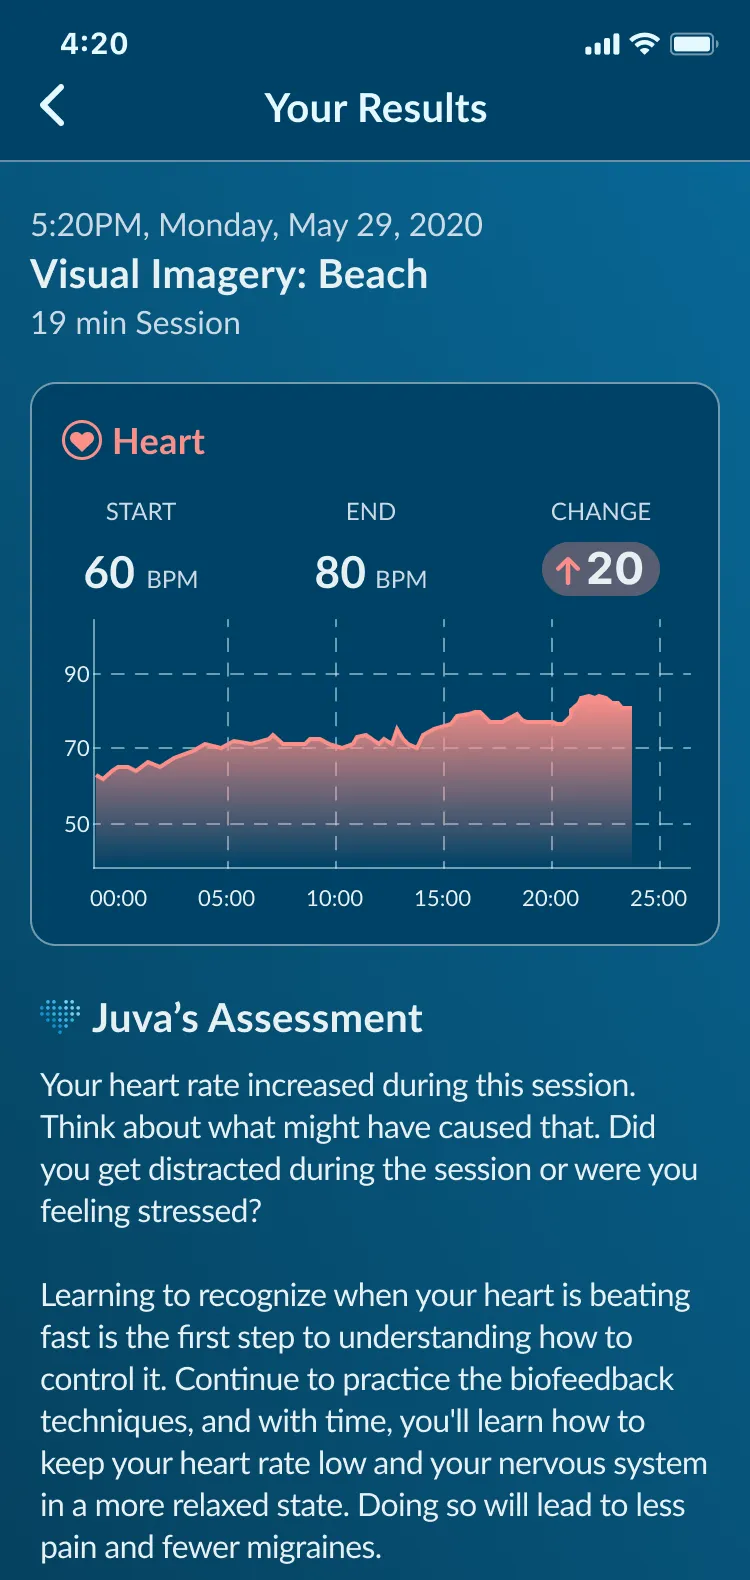
The copy got the same treatment. In 2020 the app said “Oops! Your temperature actually decreased.” What replaced it asked what might have caused it, which is the question a clinician would ask.
The ground under those instruments took two years and a correction, and it wasn’t the correction I expected. In April 2019, before there was any code, I catalogued migraine symptoms as design requirements and specced a dark interface in deep purple, on the reasoning that people with migraine may be particularly sensitive to light. That purple went into the prototype we pitched investors with and no further. What our CTO built next was the first thing that actually ran, and it was white. He wasn’t a front-end developer and he was aiming at an MVP; the design treatment came later, once there was time for it. So the app shipped white in June 2020, by which point a rebrand had already moved the company’s color from purple to navy anyway.
That August a beta tester told us the app was “very white,” light sensitivity being one of her biggest triggers. In October I ran a look-and-feel study of twelve responses from eleven people, nine of whom report or imply living with migraine. Dark navy won. One response corrected the assumption I’d carried since 2019: “High contrast is akin to bright white for me.” The problem wasn’t brightness, it was contrast, and my 2019 spec hadn’t made the distinction. The dark build landed in February 2021, on the brand navy rather than the purple I’d drawn.
The clinician, back on camera
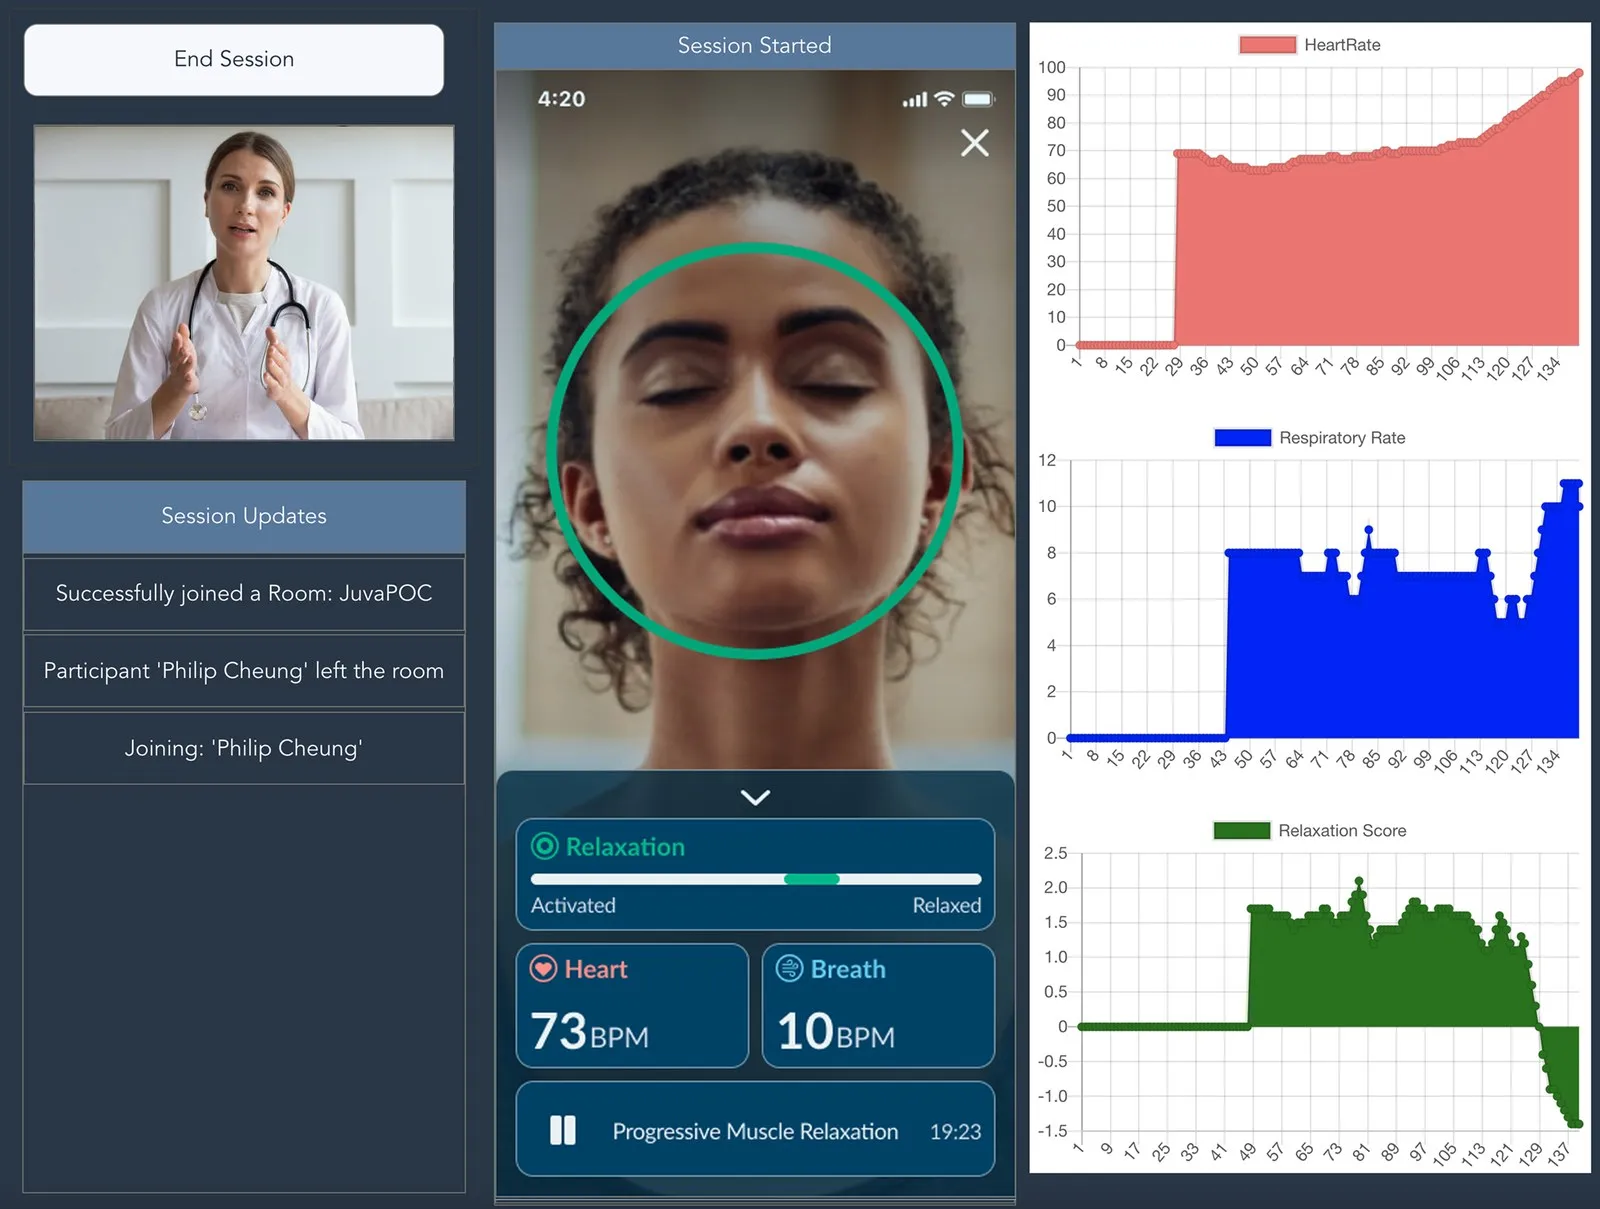
In early 2021 the CTO and I were building e-visits. The logic was financial: a clinician-led session is billable to insurance, and billable sessions could fund the self-serve product while patients practiced alone between visits. It also meant putting the clinician back on screen, which is the one thing the rest of the product had spent two years engineering around.
We ran a telehealth study with three clinicians and four patients. One clinician explained that many people become activated at the sight of a lab coat. So in a therapy that lowers arousal and then measures whether you managed it, the format that pays for the product works against the product.
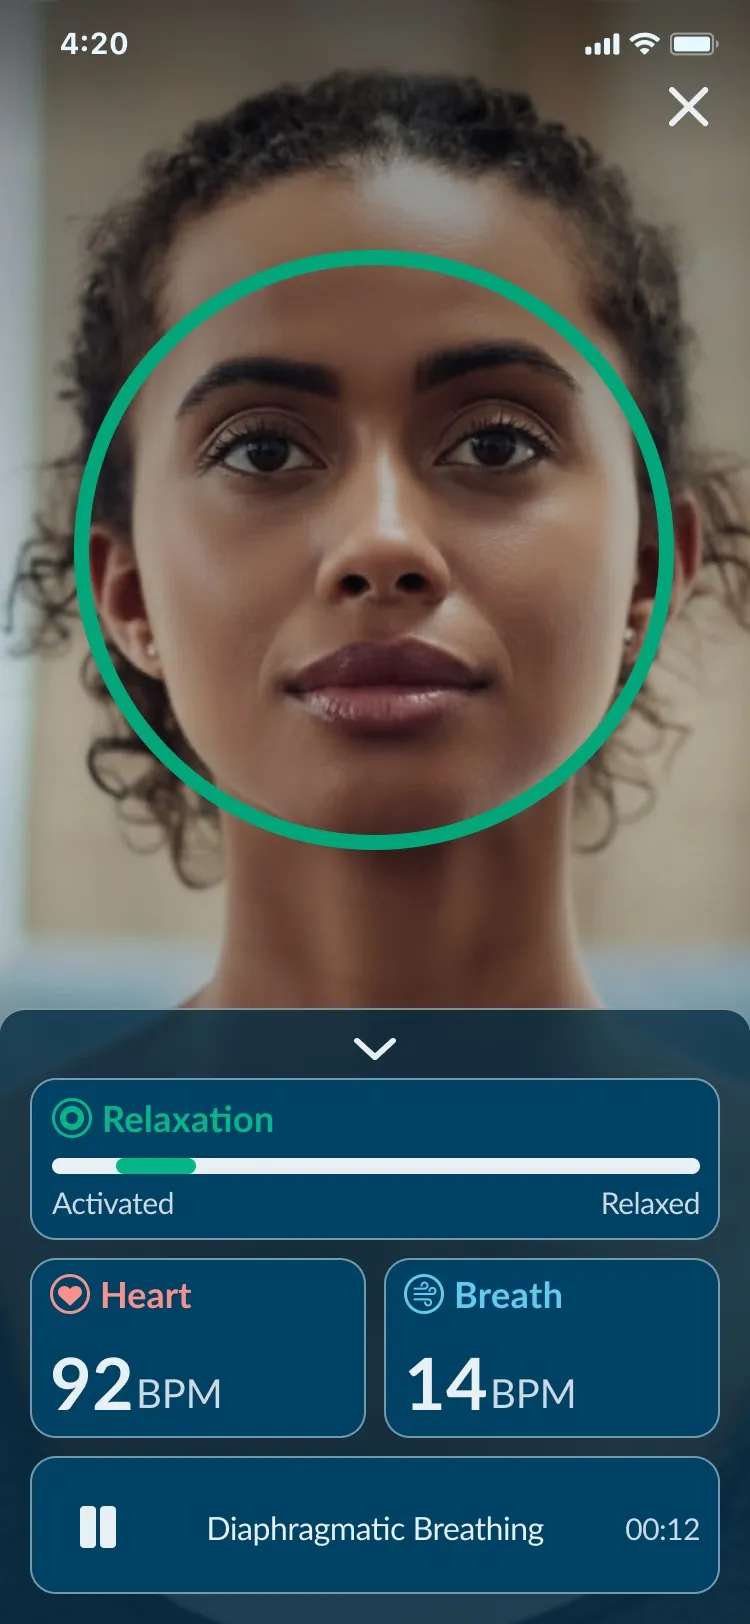
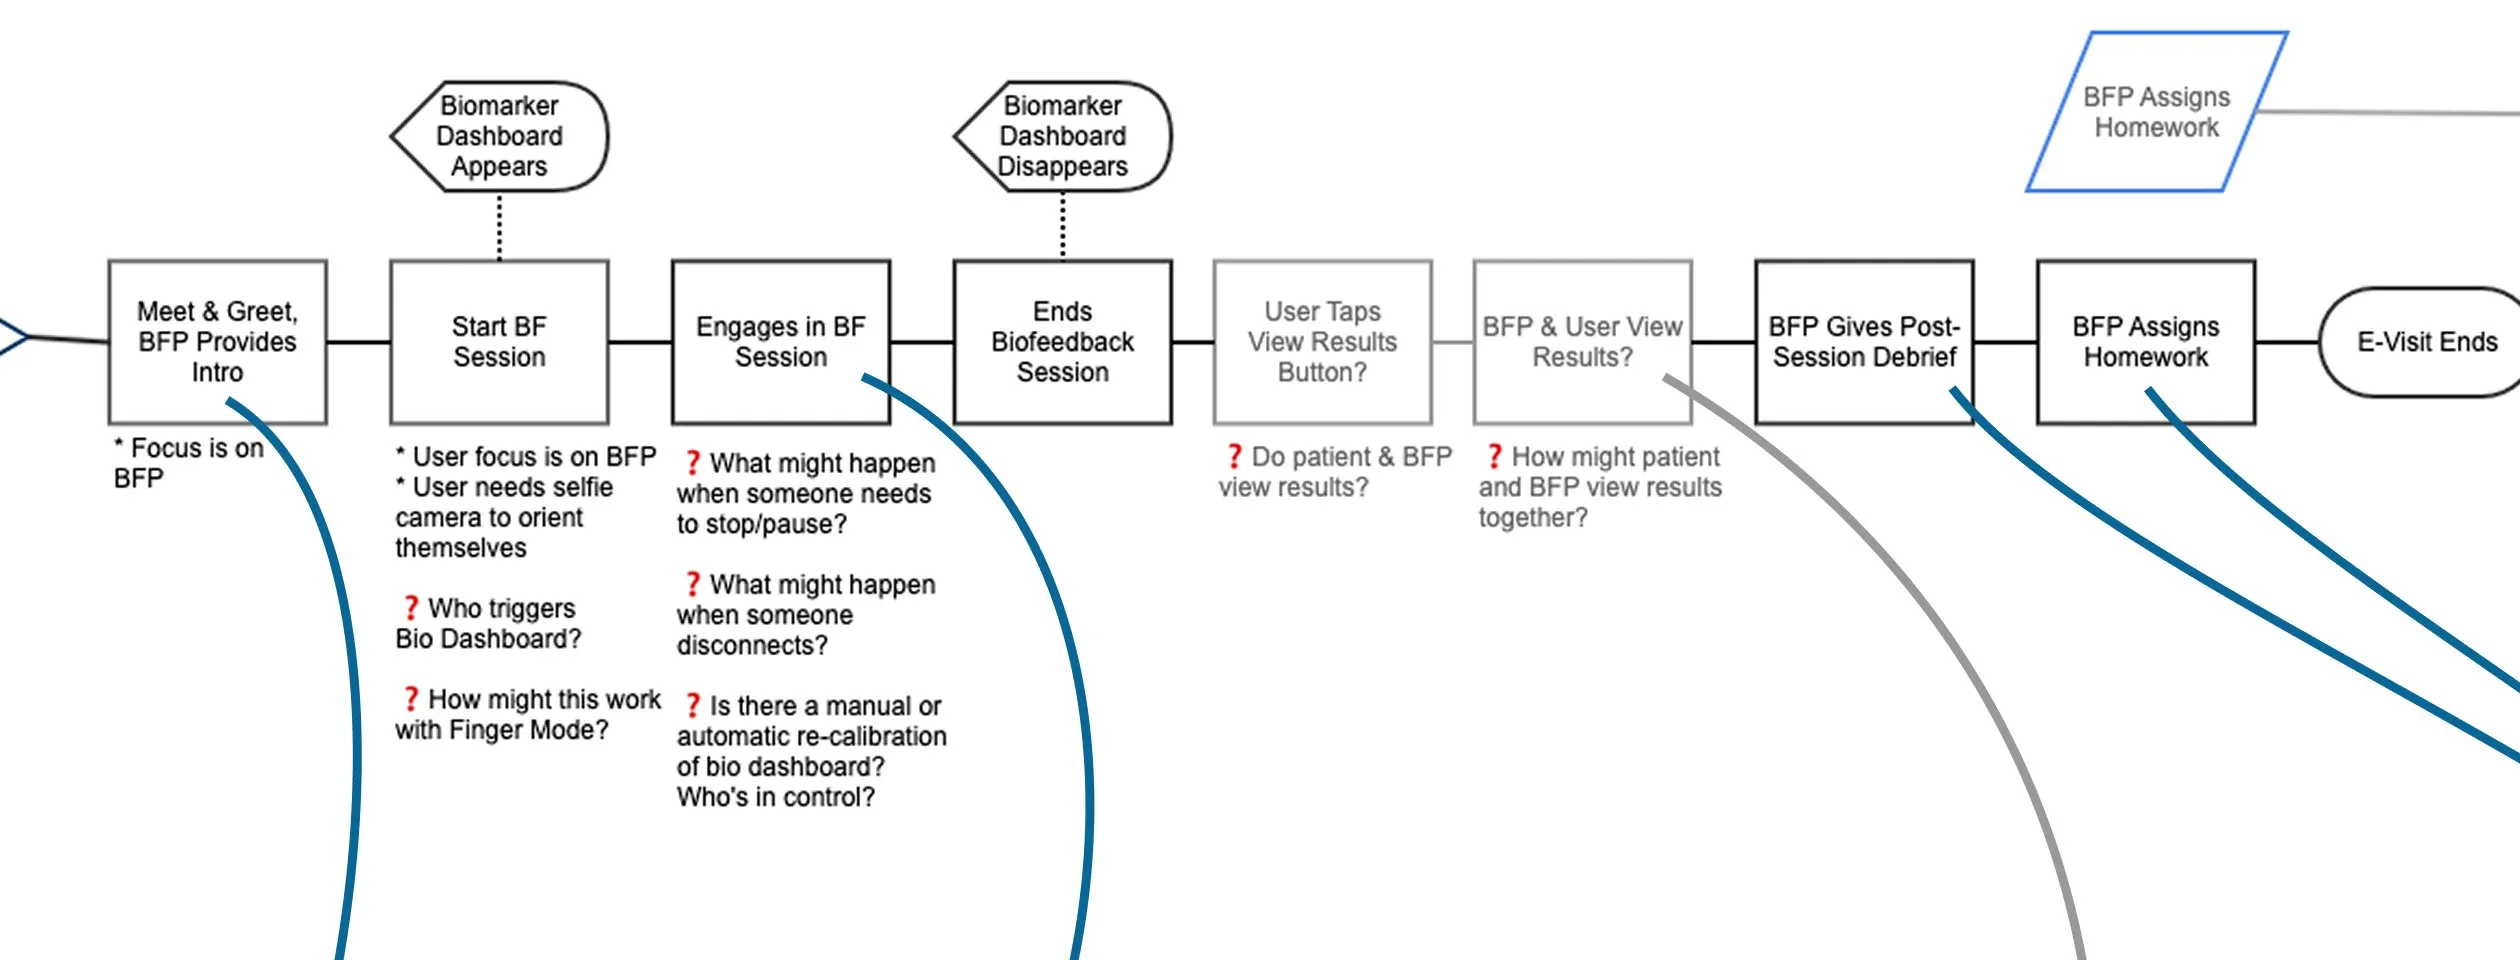
I mapped both lanes of the visit as a service blueprint, designed the patient and provider interfaces under it, and we got it running as a proof of concept: a real session, with live heart-rate and relaxation traces on the clinician’s side. The blueprint carries my open questions on it in red: who triggers the biometric dashboard, who controls recalibration, what happens when someone disconnects mid-session. They were still open when I resigned in May. It’s the sharpest problem the project handed me and the one I have least to show for.
The honest numbers
The app shipped in June 2020, referral-gated behind clinic codes, after five App Store rejections. It opened to the public in April 2021 and never reached the clinical trial that would have proven the treatment worked in this form. Ten days after public launch the numbers were modest: 396 downloads against a goal of 1,000, 89 paying users, around 30 clinics.
The design outlived my tenure. I resigned in May 2021, gave the CEO the Figma files, and offered to walk the next designer through them. That September the company shipped an “all new design”: 28 sessions, 32 games, and the 12 Week Plan, which is the 90-day program, built from the files I handed over.
What I claim, and what I don’t
Hers — the therapeutic program itself·the session recordings·the clinical thresholds, with Dr. Andrasik
Mine — the program’s structure and delivery design·the session interface and gauge·the failure-copy system·the games’ experience and feedback design·brand, curriculum, marketing site, physical kit
Worked with — the CEO, whose 2019 evaluation carried the games mechanic before my first design work·the CTO, who built the first prototype and telehealth with me·a designer I managed, who drew the first illustrations·an audio engineer·a branding consultant
The therapeutic content is Dr. Buse’s throughout. My claim is the delivery: the structure, instruments, and copy that let her program operate without her.
Reflection
The stakes here were not abstract: a vulnerable population, a real treatment, and no expert present to catch what the product got wrong. What Juva taught me is that trust in an absent expert is built out of specifics — a gauge with no failing end, a question where an “Oops!” used to be, a program that responds to a lapse the way she would have. I left in May 2021 without a number that says whether any of it worked, and the trial that would have settled it never happened. What I have is what the testers told us in September 2020, in the same conversations where they said the biomarkers jumped and sitting still hurt: that it had potential, that it was necessary for people with migraines. One of them, using it during an attack, said the pain went distant: “kind of like they give you pain medications in the ER, you could still feel it but not as acute. It wasn’t very long, just several seconds. But I thought that was cool and something worth striving for.”